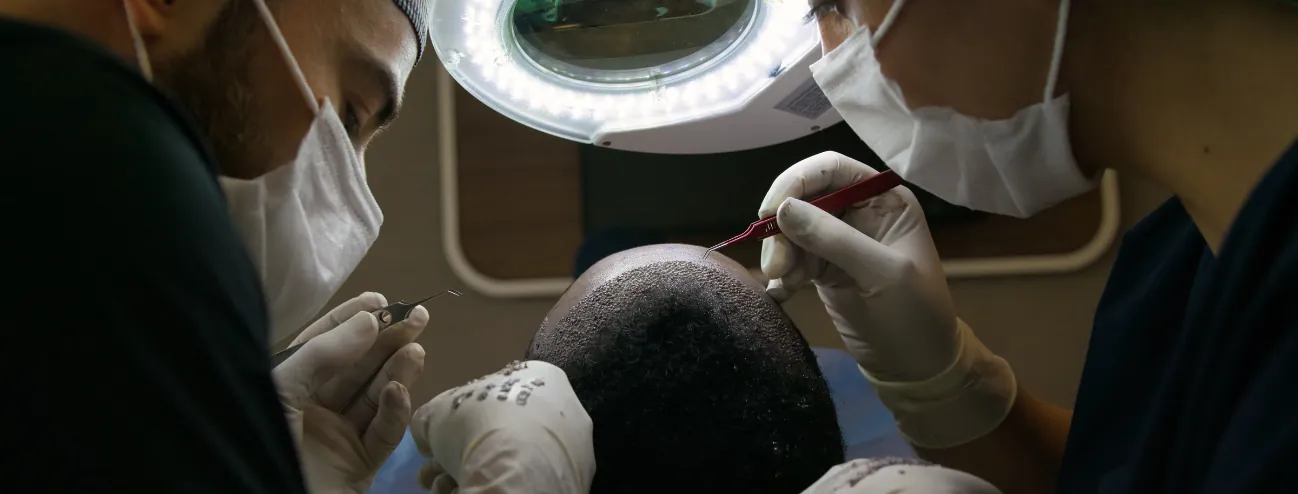
Yes, Afro hair can be transplanted, and in experienced hands the result looks natural. That applies to tightly coiled hair, curly hair and everything in between. Two things have to be in place: the surgeon must adapt the extraction to your curls, and it must first be clear whether your hair loss is caused by traction alopecia, CCCA or another scarring alopecia. The biology is the same, and you're assessed as a candidate by the same rules as every other hair type. The difference lies in the extraction technique, in how much each graft gives you, and in how thoroughly the scalp needs to be examined before anyone picks up an instrument.
This page goes deeper than the general guide to hair type and texture and the guide to who is a candidate. You'll learn why the curved follicle is harder to extract, and why your curls can still give you an advantage. We cover traction alopecia and CCCA, the two diagnoses clinics see most often in people with Afro hair, and what it means if you scar easily with keloids. After that we compare FUE, DHI and FUT, show you how to find a clinic that has done this before, and go through what is different in the weeks after the procedure.
- Afro hair can be transplanted with results as good as other hair. Curls affect the technique and the plan, not whether you're a candidate.
- The follicle curves under the skin. That raises the risk of it being cut during extraction, unless the surgeon uses a punch designed for curls, works more slowly and ideally does a small test extraction first.
- Hair loss after years of tight braids, weaves, dreadlocks or extensions, known as traction alopecia, is what most often leads people with Afro hair to ask about a transplant. The pulling must have stopped, and the area must have stayed stable.
- If you have CCCA or another condition that causes scarring on the scalp, a dermatologist must have made the diagnosis, and the condition must have been quiet for at least six months before anyone operates.
- If you or someone in your family has had keloids or thickened scars, you can still have surgery. The plan changes, and it usually points towards FUE and away from FUT.
Can Afro hair be transplanted, and is the result as good?
Yes. With an experienced surgeon, the result in Afro hair is as natural and lasting as in other hair types. Curls affect the extraction and how many grafts an area needs, but whether you're a candidate still depends on whether your hair loss has stabilised and whether you have enough healthy donor hair.
Results in Afro hair aren't worse by nature. The difference lies in the work that leads up to them. The curved follicle makes extraction harder, and we'll come to that in the next section. The same curve gives the curls more coverage once they're growing in place. A good plan uses that quality on purpose.
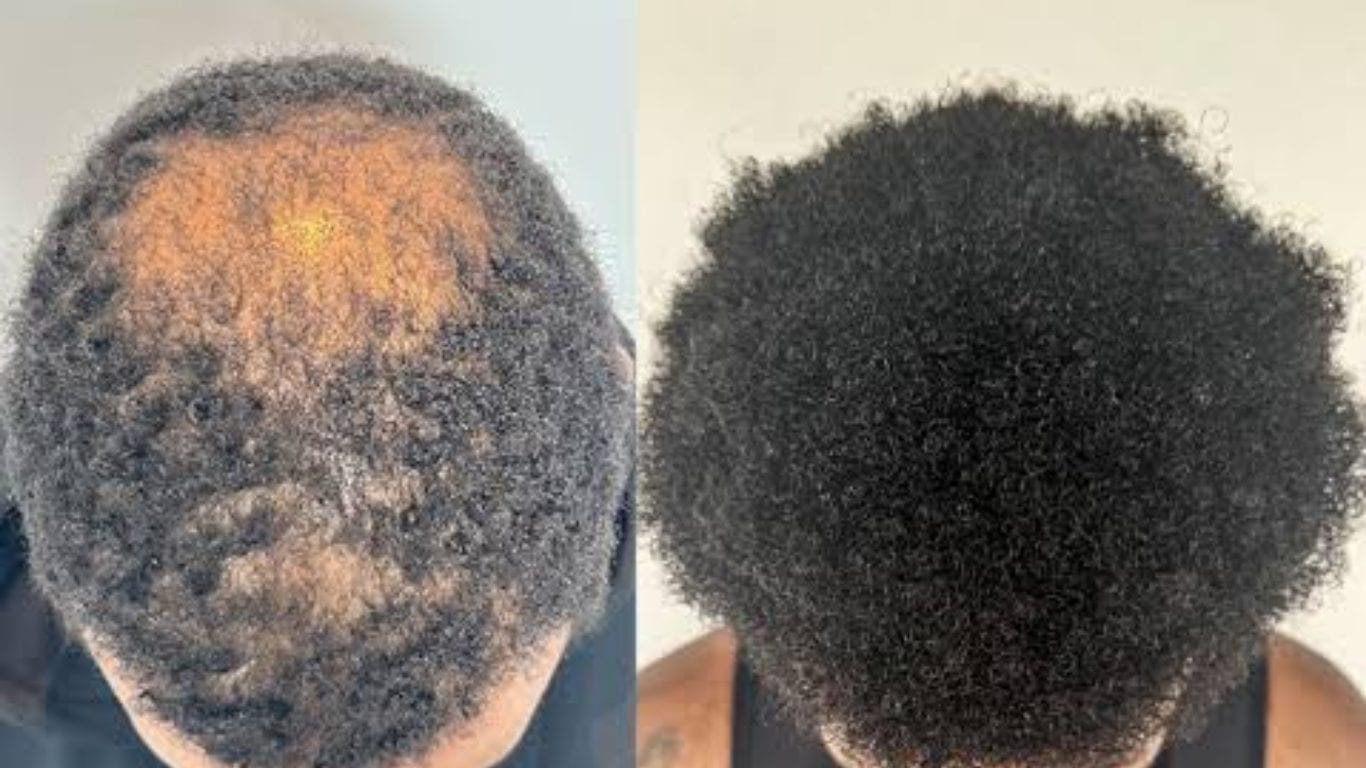
What decides whether you're a candidate?
There are two requirements, and they apply whatever your hair type. Your hair loss must have a stable pattern and not be diffuse, active thinning. The hair at the back and sides of your head must be genetically resistant, and it must be dense and thick enough to fill the area that has lost hair. Curls, texture and ethnic background change none of these requirements. That's why neither the candidate guide nor the guide to hair type and texture treats Afro hair as a separate group when it comes to who can have surgery. It's only a separate group when it comes to technique.
Does the result last as long?
Yes, for the same reason as for everyone else. The grafts are taken from the donor area at the back of the head, where hair withstands DHT better than at the hairline and the crown. DHT is the hormone behind most cases of hereditary hair loss. No follicle is completely immune, so an honest clinic won't promise that it lasts forever. It's the relative resistance that makes the grafts hold, in curly hair just as in straight.
Where do you need to be extra careful?
Before the procedure itself. Someone has to establish what kind of hair loss you have. Is it traction alopecia, CCCA or another scarring condition, or is it ordinary hereditary hair loss? Each one leads to a different next step, and usually only hereditary loss can be operated on straight away. The rest of this guide looks at each of them.
Why is it harder to extract grafts from curly Afro hair?

The follicle curves under the skin, sometimes by almost 180 degrees, and an ordinary straight FUE punch cuts it more easily further down than in straight hair. This is called transection. Experienced surgeons deal with it by using a punch adapted to curls, often larger or with a flared tip, working at a slower pace and often doing a small test extraction before the full session.
Even when hair looks only wavy above the skin, the root beneath the surface can follow a clear curve. An ordinary FUE punch goes straight down. When the root bends away, the punch can neither see nor follow the bend, so it's easy to cut through the follicle further down. A transected graft has poor odds of survival.
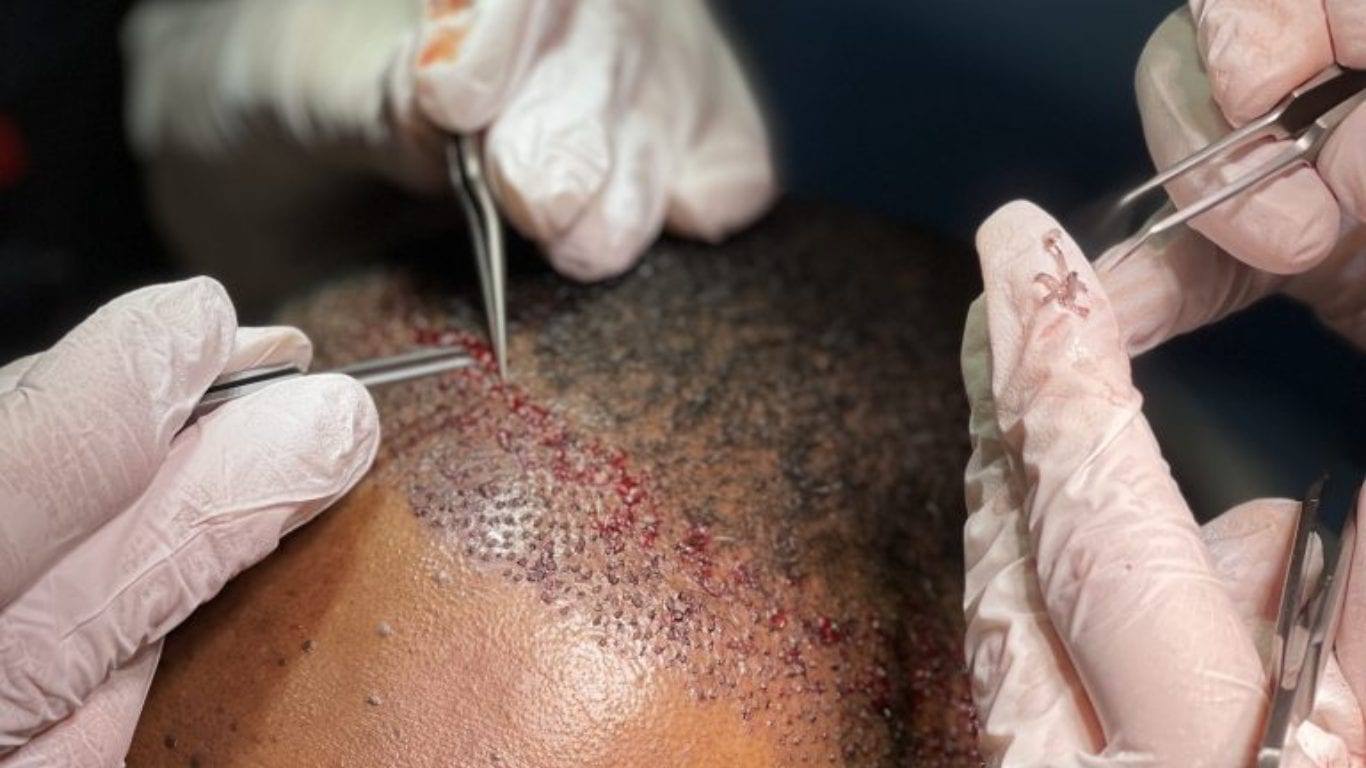
How does the surgeon adapt the punch and technique?
Surgeons who often work with Afro hair tend to choose a slightly larger punch, one with a flared tip or one with a blunt tip, which follows the curve and cuts less. They adjust the angle and depth for each patient and spend more time on each graft so fewer follicles are cut. None of this needs special equipment. It's a learned adjustment of standard tools, which is why the surgeon's own experience with this particular texture tells you something about how many grafts you'll lose. The total number of FUE procedures the clinic performs tells you much less.
What does a test extraction show?
How often the follicle gets cut varies a lot from person to person when hair is tightly coiled. Some experienced clinics therefore extract a small number of grafts first, often anything from a few dozen up to around 100, before deciding on a full session. That lets the surgeon see how your particular curls respond to the punch, and how many of your follicles are cut. It's a cheap question to ask at the consultation. Not every clinic offers it.
Does this mean the result will be worse?
No. It means the surgeon's experience with curly hair decides what proportion of the grafts survive and grow. The number of attempts says little about that. Even if your donor area has normal density, between 65 and 85 follicular units per cm², the yield can be disappointing if many roots are cut. That's why a test extraction is worth asking about. You can read more about density and yield in the guide to donor hair. For curly hair the main point is simple: it's the actual transection rate, not a high graft count in the quote, that determines your result.
Why can Afro hair look denser with fewer grafts?
A curly strand coils and bends back on itself instead of lying flat, so each graft hides more scalp than a graft of straight hair does. It casts more shadow and looks fuller to the eye. With pronounced curls you can therefore often manage with somewhat fewer grafts than with straight hair.
It may sound like the opposite, but it's a real advantage that offsets the risk during extraction. The curls that make grafts harder to extract also make each graft fill more once it grows. A straight hair lies flat and covers roughly its own width. A tightly coiled hair of the same length winds itself into several loops, takes up much more space and creates shadows between the strands. The eye reads that as denser hair.
Is the graft count the most important number?
No. Imagine two people with exactly the same number of viable grafts. One has fine, straight hair, the other tightly coiled Afro hair. Once the hair has grown out, the one with curls usually looks fuller. That's why comparing graft numbers between hair types gives a skewed picture, and why the target for an area with pronounced curls can often be set lower than for straight hair.
Do curls help the hairline too?
Yes. An edge that's slightly irregular looks natural. A line drawn with a ruler doesn't. Curls create that soft edge almost by themselves, and the surgeon gets a little more leeway than with completely straight hair.
How do you find your own number?
The advantage doesn't remove the extraction problem. The two effects pull in opposite directions: harder to extract intact, but more forgiving and better at covering once the grafts are in. The graft calculator gives you a rough estimate. Curls, however, are exactly the kind of factor an area-based formula doesn't capture. A correct number needs someone to look at your hair.
It depends on your donor area, your hair type and where the loss is. Send three photos and the medical team at the clinic at the top of our ranking will suggest a method and number of grafts.
Goes to the clinic at the top of our ranking.
Is hair loss from tight hairstyles the most common reason people with Afro hair want a transplant?
Yes, usually. Traction alopecia is hair loss caused by long-term pulling from tight braids, weaves, dreadlocks, extensions or a tight ponytail, and it most often shows as thinning along the hairline and at the temples. Early on it can reverse without surgery, and once the pulling has stopped and the area has stayed unchanged for a while, it's a good and common reason for a transplant.
Traction alopecia is caused by pulling on the hair over a long time, not by hormones. It's mechanical damage rather than a hereditary pattern, so it behaves differently from the hereditary hair loss the rest of this site is about. It often starts almost unnoticed, with an edge that has receded a little or thinned out at the hairline and around the ears. If you keep wearing the styles that caused it, it gradually gets worse.
Does traction alopecia reverse?
Early on, yes. As long as the follicle is stressed but still alive, the hair often comes back once the pulling stops. Switching to looser styles, taking longer breaks from protective styles or giving up braids, weaves and extensions for a while can be enough. If the pulling has gone on for years, the follicle can die and be replaced by scar tissue. Then the hair won't come back by itself, and a transplant is the only way to regain density. The guide to causes of hair loss explains this pattern in more detail.
When are you ready for a transplant?
Two conditions must be met. The hairstyle that caused the loss must have stopped, or changed enough that the pulling is gone. And the area must have stayed unchanged for a good while, with no visible worsening. If surgery is done where the hair is still being pulled, or where the loss hasn't settled, the result may look good now and thin out again after a few years if the habit continues. With hereditary hair loss, most clinics wait until you're around 25 and the loss has settled. Traction alopecia is mechanical, so here what counts is whether the pulling has stopped. Age alone tells you little.
Why does the scalp need to be examined first?
Long-standing traction alopecia can at first glance look like CCCA, which scars the scalp and is the topic of the next section. The two are treated very differently, so it must be clear which one you have before anyone draws up a plan. Traction alopecia is also a common cause of hair loss in women, though not only in women. In women, tight hairstyles are one of the clearly defined causes that respond well to a transplant once the loss has stabilised.
Can you have a transplant if you have CCCA or another condition that scars the scalp?
CCCA, central centrifugal cicatricial alopecia, scars the scalp and affects people with Afro hair more often, especially women. It starts at the crown, spreads outwards and destroys the follicles permanently. The diagnosis is made by a dermatologist, and the condition must have been quiet for a long time, often one to two years, before surgery, because grafts placed in active disease often die and can trigger a new flare.
With CCCA, it's the condition itself that creates the scars. It usually starts in the middle of the crown, spreads outwards in ever larger circles and turns the follicles into scar tissue as it goes. Other conditions in the same group are discoid lupus, lichen planopilaris and frontal fibrosing alopecia, and the candidate guide covers them together. CCCA is still more common in people with Afro hair, and mostly in women, than in the population as a whole.
Why is active disease the big problem?
The grafts aren't rejected, because they're your own tissue throughout. The problem is that grafts placed in inflamed tissue with ongoing scarring have a poorer chance of survival. The procedure itself can also make the underlying condition flare up in the surrounding skin. As long as the condition is active, neither risk is worth taking.
Why must the condition have been quiet for six months?
With CCCA and similar conditions, a transplant is only considered once your dermatologist has confirmed that the condition has been quiet for at least six months, and you're still attending follow-ups. That's more than a formality. It's the line between a procedure where the grafts have a real chance and one where you risk losing the grafts and waking the condition up again.
Who should you see first?
A dermatologist. Early CCCA can at first glance look like traction alopecia or ordinary thinning, and what you should do next depends entirely on what it actually is. If you notice thinning at the crown that is slowly spreading, especially if your scalp is tender, itchy, burning or looks changed, you should get a diagnosis from a dermatologist before you go to a hair transplant clinic. Don't skip that step. With a confirmed and quiet diagnosis, the surgeon can plan based on facts.
Can you have a hair transplant if you get keloids or thickened scars easily?
Yes, but the plan changes. Keloids and hypertrophic scars are described more often in people with Afro hair and dark skin, so the clinic should ask carefully about your own and your family's history, mainly because it affects how the donor area heals. That's why the surgeon usually chooses FUE, which leaves small dots, and avoids the long incision of FUT.
A keloid is a raised, thick scar that spreads beyond the original wound, sometimes a lot, and it can itch and ache. A hypertrophic scar is similar but stays within the edge of the wound. Both have to be taken into account when planning any operation, including a hair transplant. Both the extraction and especially the closure of a donor wound create small wounds that heal in the same way as any other.
Why is the donor area most at risk?
With FUT (strip method), a strip of scalp is removed and the wound is closed with one long incision. In someone who is prone to it, exactly that kind of wound is a typical site for a keloid or hypertrophic scar. A thick scar at the back of the head is harder to live with than many others. It limits which hairstyles you can wear, for example a very short cut or a shaved head, and it's hard to hide.
Why is FUE chosen more often here?
FUE extracts individual follicles through small round holes spread across the donor area, with no long incision. The holes heal into small dots that are far less visible. The risk of one large, visible keloid in the donor area becomes clearly lower, though it doesn't disappear completely. If you have a known tendency to keloids, FUE is therefore usually what the surgeon leans towards. Some clinics also start with a small session and see how your scalp heals before planning a larger one.
What does a thorough clinic ask about?
Whether you've had a keloid or thickened scar after a cut, a piercing, a vaccination or an operation. Whether anyone in your family has, because the tendency is partly hereditary and a strong family history counts even if you've never had one yourself. And what skin type you have. The answers aren't an exam you can fail. They're used to choose the technique and the size of the session, and they don't mean surgery is ruled out. What else a thorough assessment before surgery should cover is in the guide to red flags.
Which method suits Afro hair best: FUE, DHI or FUT?
FUE is the most common choice for Afro hair, because small dot scars spread out carry far less chance of a large keloid than the scar line left by FUT. DHI extracts grafts the same way as FUE and so doesn't lower the risk of cut follicles, but the precise placement can help when hair grows in many directions. FUT can still work well when the curls are very tight, since the strip is divided under a microscope, but you get a scar line.
What matters isn't the name of the method. It's what it changes for curly hair: how the follicle is extracted, and how visible the scar becomes. You've read about both earlier in this guide.

Why is FUE the first choice for most people?
With FUE, grafts are extracted one by one with a small punch. What's left is scattered dots that rarely show, and no line. If you get keloids easily, that's why most surgeons choose FUE. The downside, as you read above, is that the curved follicle carries a higher risk of transection during extraction. The surgeon must use a punch adapted to curls and work carefully without rushing.
What does DHI change, and what doesn't it change?
With DHI, follicles are usually extracted with the same type of punch as in FUE. The difference lies in the placement. An implanter pen opens the skin and places the graft in a single movement, and the surgeon controls the angle, direction and depth closely. In Afro hair, which more often than straight hair grows in several directions, that control can be a real help. But DHI does nothing about the risk of cut follicles, because the extraction is the same as in FUE. Your transection rate depends on how the follicle is extracted. How it's placed doesn't affect it.
When is FUT a good choice?
With FUT, a strip of scalp is removed from the donor area and divided into grafts under a microscope. The team can then see the curve in each follicle and doesn't have to follow it blind through the skin. When the curls are very tight, this can mean few cut follicles and many grafts in one go. The price is a scar line in the donor area. That weighs heavily if you get keloids easily, or if you want very short hair at the back of your neck. So FUT is a real option with its own pros and cons, not an inferior solution.
What should decide the choice?
None of the methods predicts your result on its own. What does is the team's documented experience with extracting and placing Afro hair. If you want to compare FUE, DHI, FUT and sapphire FUE more generally, you'll find that in the methods guide.
How do you choose a clinic for an Afro hair transplant?
Ask for before-and-after photos of patients with Afro hair or tight curls, and ask how many such procedures the team that will operate on you has done itself. A clinic that knows this work talks without hesitation about transection rates, punch technique and whether you can have a test extraction.
Everything you've read so far, about cut follicles, extra coverage, traction alopecia, CCCA and keloids, comes down to one question for the clinic. Does this team have proven experience with Afro hair, and not just with hair transplants in general?

What should you ask for?
- Patients with Afro hair in their portfolio. Before-and-after photos of tightly coiled or Afro hair. A gallery that shows almost only straight hair says little about what they can do for you.
- How much experience the team really has. How many patients with exactly this texture have the people who will operate on you treated? The number the clinic uses in its marketing covers the whole clinic.
- A clear answer about the punch. What type of punch, what size and what angle do they choose for tight curls, and why?
- Test extraction. Do they offer a small test extraction before the full session, and how do they measure and tell you how many follicles were cut?
- Working with a dermatologist. Does the clinic ask about your diagnosis, and can it refer you on before operating in an area where you've had tight styling or scalp problems?
Why does this matter more than graft count and price?
A high graft count in the quote is worth little if many follicles are cut in tightly coiled hair. A damaged graft won't survive, however many extractions were made. What counts is viable grafts placed correctly in your particular texture. That has much more to do with experience of curly hair than with how large the clinic's sessions are or what price level it sits at. The general checklist, with a named surgeon, accreditation you can verify and open pricing, is in the guide to red flags. The questions above come on top of that.
Where do you start?
Take sharp close-up photos in daylight of the area where you've lost hair, the donor area and any places where you've had pulling or scarring. That lets an experienced team give you a useful first assessment of your texture and a realistic graft count before you've booked any travel. Read how to choose a clinic step by step, compare in the ranking and look through the clinics we recommend. Take the Afro hair questions to the ones left on your shortlist.
How are the weeks after the procedure different when you have Afro hair?
Healing follows the same timeline as for everyone: the new hairs shed in weeks 2 to 3, growth picks up again between months 3 and 4, and after about 12 months you can see how it turned out. The difference is in your daily routine, with fewer and milder products in the first weeks, and no tight braids, weaves, dreadlocks or wigs until the grafts are firmly anchored.
Grafts heal the same way in Afro hair as in any other hair. The routine around them is different. Afro hair is usually cared for with more product and more handling, and more often put up in tight styles, than straight hair. All of that needs to change in the first weeks.
How should you use moisture and products at first?
At first, both the donor area and the new area need to be kept clean. Heavy oils, hair butters and styling products should wait while small scabs form and the grafts settle. Most clinics give you a dedicated, gentle washing routine for this period. Once the clinic has seen that the area has healed, you can usually go back to your normal moisturising. Heavier products are best brought back gradually.
When can you go back to protective styles?
Tight braids, weaves, dreadlocks, extensions and wigs that pinch or pull near the new grafts or the donor area put strain on exactly the places where the grafts are trying to establish a blood supply. It's the same mechanism that caused the traction alopecia in the first place. There's no date that applies to everyone. The grafts are still anchoring when the new hairs shed after 2 to 3 weeks. Most clinics ask you to keep tight styles away from the treated area for much longer, often for months. Your clinic decides at your follow-ups when it's safe for you.
Is the growth timeline the same?
Yes. Around weeks 2 to 3 the new hairs fall out. That's supposed to happen and doesn't mean the grafts have failed. Between months 3 and 4 new hairs start to appear, and after about 12 months you see the result, both the density and how the hair sits. The general advice, such as how to sleep, wash and exercise, applies to all hair types and is in the aftercare guide. Here we've only included what is specific to Afro hair.
How do you look after the result over time?
Traction alopecia comes from habits. For the result to last through the years, you need to change the hairstyles that caused the thinning for good. A break isn't enough. Otherwise the same applies as for any transplant: look after the hair you have around the grafts, expect your hair to age like all other hair, and go for check-ups at regular intervals. Read more about how long the result lasts.
Questions we often get
Will I have visible scars after an Afro hair transplant?
Usually very little. FUE leaves small, scattered dots that rarely show once healed, even with a short cut. FUT leaves one scar line, which is a bigger drawback if you get keloids easily or want very short hair at the back and sides. That's why FUE is usually the first choice for Afro hair.
Can hair be transplanted straight into braids, dreadlocks or a weave?
No. A transplant moves living hair roots from one place on your head to another. No hair is attached to braids, dreadlocks or a weave, and grafts only survive when they sit in healthy skin. The procedure can recreate a hairline or fill an area that traction alopecia has thinned, as long as the pulling has stopped and the loss has been stable for a while. You get back your own hair that grows. You don't get a hairstyle.
Does transplanted hair keep its curls?
Yes. The curl pattern, like thickness and colour, is built into the hair itself and not the place it grows. A graft keeps its curls when it grows in its new location, just as donor hair keeps its texture when transplanted to a beard or eyebrows.
Is a hair transplant safe for Black women?
Do I need to pause relaxers, texturisers or other chemical treatments?
Yes, usually. The clinic wants a calm, clean scalp without irritation before the procedure. Strong chemical treatments such as relaxers (chemical straightening), hair dye and a lot of heat styling near the donor area and the new area are therefore often paused for a while before and after. How long depends on your scalp, so the clinic decides.
How many grafts do I need with Afro hair?
There's no separate number for Afro hair. The number depends on how large the area is, how dense your donor area is and how thick your hair is, as with every hair type. Curly hair often covers more scalp per graft, so the target for an area can be somewhat lower than with straight hair. You only get a number you can trust once someone has looked at your donor area and your curls.
Is a hair transplant more expensive for Afro hair?
Not automatically. The number of grafts and the clinic's pricing model still drive most of the price, not your hair type. The difference may lie in time. A slower, more precise extraction in tightly coiled hair can take longer per graft, and some clinics factor that in when they plan the session. Ask the clinic directly. Don't assume the price per graft is the same as for straight hair.
How high your risk of cut follicles is, how many grafts you need, and whether your thinning is caused by traction alopecia, CCCA or ordinary hereditary hair loss, you'll only find out when someone looks at your scalp. Ask for a free hair analysis, and the clinic ranked number 1 on our list will look at your hair and scalp and tell you honestly what is possible. You're not committing to anything.
This is general information and not medical advice. Only a qualified surgeon, possibly together with a dermatologist, can tell you after a personal assessment whether you're ready and what your hair can achieve.
Goes to the clinic at the top of our ranking.
Updated: October 2026 · How our editorial team works